
Why Is Astaxanthin Studied for Cardiovascular Protection?
Keyora Research Q&A Library
This is part of the Keyora Research Q&A Series, derived from Keyora Astaxanthin Research Journal Series.
Within the Keyora Astaxanthin Researcn framework, this Q&A translates complex astaxanthin biology into reader-friendly, evidence-bound answers, focusing on natural astaxanthin identity, molecular structure, antioxidant and redox mechanisms, membrane lipid interaction, mitochondrial resilience, inflammatory signaling pathways, human evidence interpretation, and the scientific principles behind responsible supplementation.
First published by Keyora Research Journal: www.keyorahealth.com

Direct Answer
Astaxanthin has attracted cardiovascular research because its antioxidant biology intersects with several processes that influence lipid and vascular health
Astaxanthin is studied for cardiovascular protection because its biological effects intersect with several processes that are relevant to cardiovascular physiology: lipid oxidation, vascular oxidative stress, inflammatory signaling, lipid metabolism, and vascular function.
That does not mean Astaxanthin has been proven to prevent cardiovascular disease.
The more accurate conclusion is that its molecular properties provide a plausible cardiovascular rationale, while human studies have reported changes in selected oxidative, inflammatory, metabolic, and hemodynamic endpoints.
The research pathway can be summarized as:
Astaxanthin
↓
Lipid-associated antioxidant activity
↓
LDL oxidative resistance
Vascular redox regulation
Inflammatory biomarkers
Lipid metabolism
Vascular-function measures
↓
Cardiovascular research relevance
The Keyora source organizes its cardiovascular discussion around several of these same mechanisms, beginning with LDL oxidation and extending into inflammation and vascular biology.
This distinction is important because “antioxidant” is not itself a cardiovascular outcome.
An antioxidant may influence molecular processes that are relevant to cardiovascular health without being proven to prevent myocardial infarction, stroke, or cardiovascular death.
The strongest interpretation is therefore not:
Astaxanthin prevents heart disease.
It is:
Astaxanthin is a biologically plausible cardiovascular nutrient that has been studied across multiple intermediate pathways relevant to vascular health.
That is the evidence question this article examines.

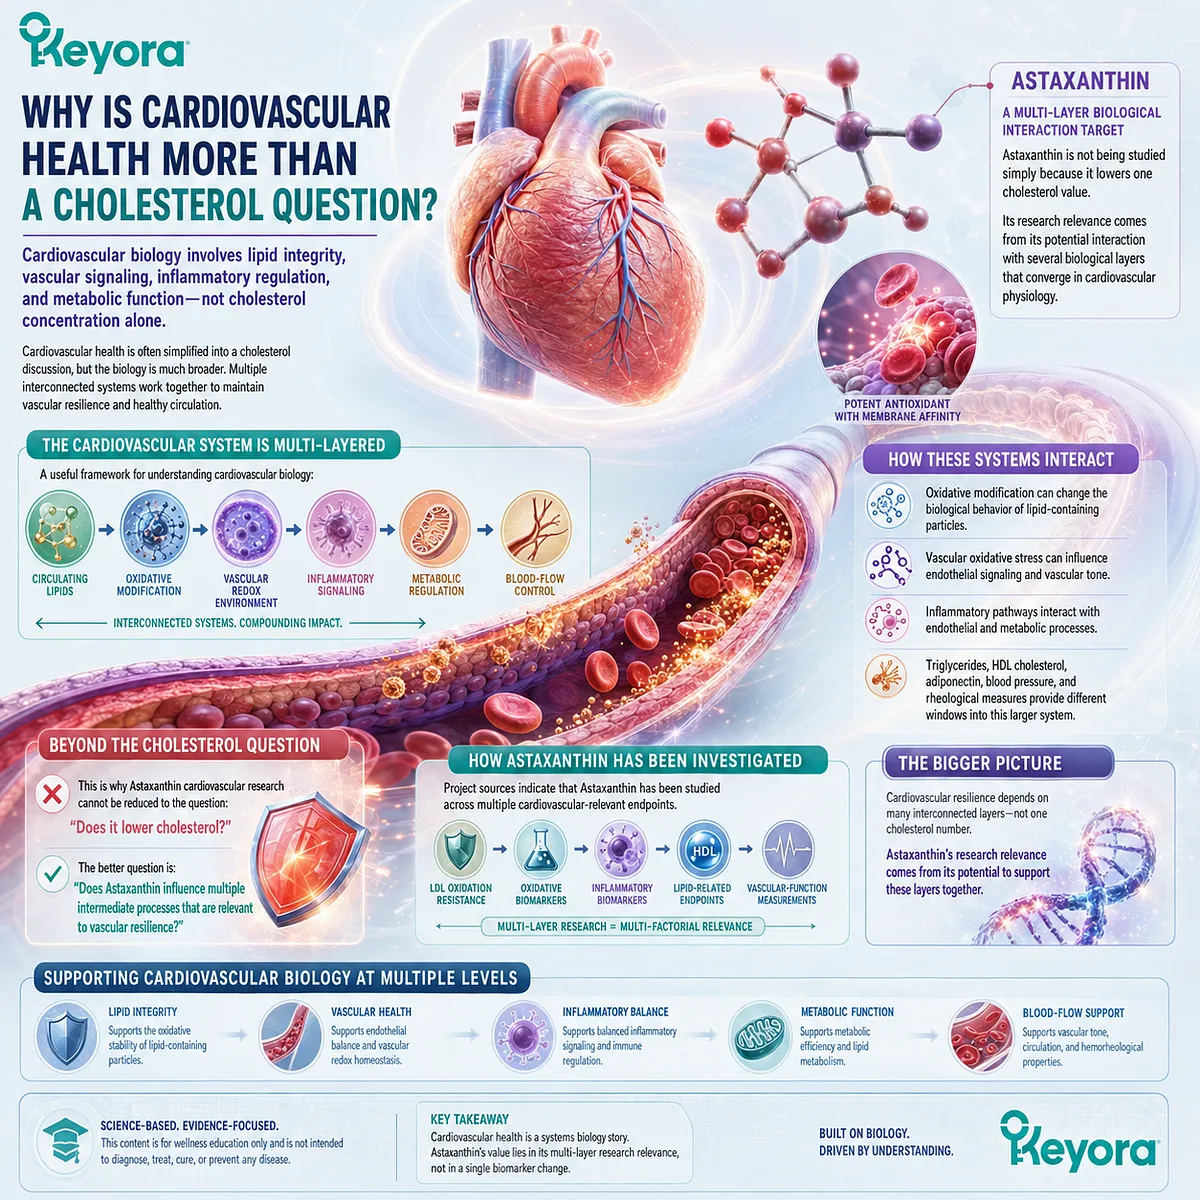
Why Is Cardiovascular Health More Than a Cholesterol Question?
Cardiovascular biology involves lipid integrity, vascular signaling, inflammatory regulation, and metabolic function—not cholesterol concentration alone
Cardiovascular health is often simplified into a cholesterol discussion, but the biology is much broader.
Circulating lipoproteins matter, yet cardiovascular physiology also depends on the condition of the vascular endothelium, the oxidative environment surrounding lipids and vessel walls, inflammatory signaling, vascular tone, and metabolic regulation.
This matters for understanding why Astaxanthin became a cardiovascular research target.
Astaxanthin is not being studied simply because it lowers one cholesterol value. Its research relevance comes from its potential interaction with several biological layers that converge in cardiovascular physiology.
A useful framework is:
Circulating lipids
↓
Oxidative modification
Vascular redox environment
Inflammatory signaling
Metabolic regulation
Blood-flow control
These processes are interconnected.
For example, oxidative modification can change the biological behavior of lipid-containing particles. Vascular oxidative stress can influence endothelial signaling. Inflammatory pathways can interact with endothelial and metabolic processes. Triglycerides, HDL cholesterol, adiponectin, blood pressure, and rheological measures provide different windows into this larger system.
This is why Astaxanthin cardiovascular research cannot be reduced to the question:
“Does it lower cholesterol?”
The better question is:
Does Astaxanthin influence multiple intermediate processes that are relevant to vascular resilience?
The available project sources suggest that this is precisely how the ingredient has been investigated: through LDL oxidation resistance, oxidative and inflammatory biomarkers, lipid-related endpoints, and vascular-function measurements.
That multi-layer research rationale is more meaningful than treating one blood lipid number as the whole cardiovascular story.
Why Is LDL Oxidation a Major Astaxanthin Research Target?
LDL oxidation connects lipid peroxidation with vascular biology, making oxidative resistance of LDL an important Astaxanthin research endpoint
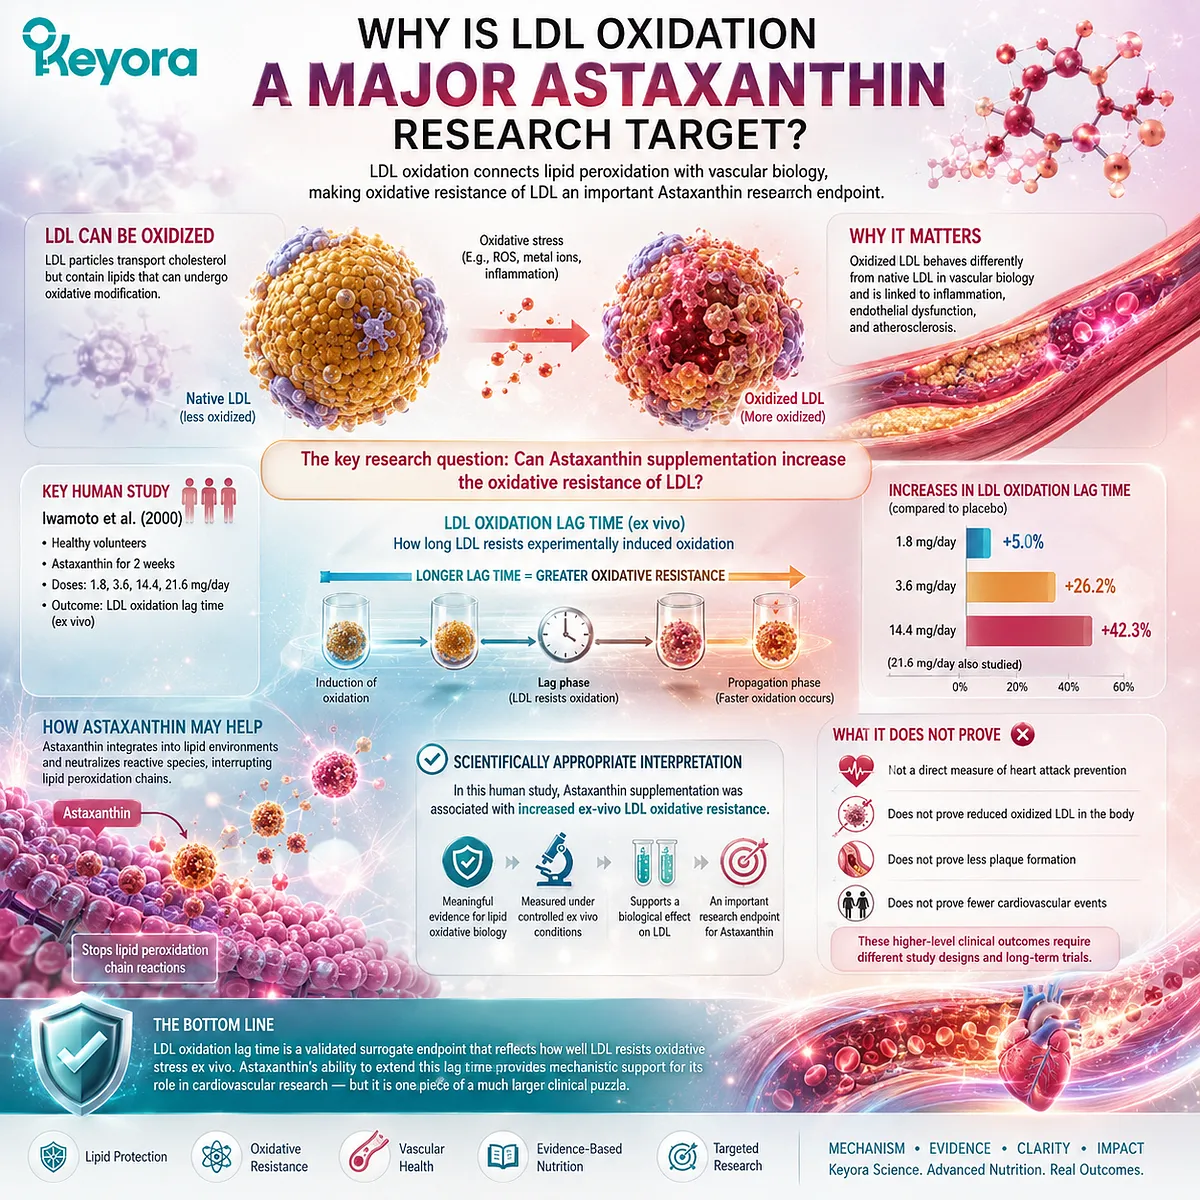
LDL particles contain lipids that can undergo oxidative modification.
This is where the earlier discussion of lipid peroxidation becomes relevant to cardiovascular research.
A lipid-containing particle can exist in a relatively unmodified state and later undergo oxidative changes. Oxidatively modified LDL is studied because it behaves differently from native LDL within vascular biology.
Astaxanthin research therefore includes the question:
Can supplementation influence the oxidative resistance of LDL?
One of the most important human studies cited in the Keyora source is Iwamoto et al. (2000).
According to the project source, healthy volunteers consumed Astaxanthin at 1.8, 3.6, 14.4, or 21.6 mg per day for two weeks. The study measured LDL oxidation lag time, and the source reports increases of approximately 5.0% at 1.8 mg, 26.2% at 3.6 mg, and 42.3% at 14.4 mg.
The meaning of this endpoint needs to be stated carefully.
Oxidation lag time does not measure heart-attack prevention.
It describes how long LDL isolated from participants resisted experimentally induced oxidation under the study conditions.
The Keyora summary itself identifies this metric as the duration that LDL particles resist oxidation ex vivo.
Therefore, the scientifically appropriate interpretation is:
Astaxanthin supplementation was associated with increased ex-vivo LDL oxidative resistance in that human study.
That is meaningful evidence for lipid oxidative biology.
But it is not equivalent to proving that Astaxanthin prevented oxidized LDL formation throughout the body, prevented plaque formation, or reduced cardiovascular events.
Those are higher-level clinical questions that require different study designs.
Why Could Astaxanthin Matter to the Vascular Endothelium?
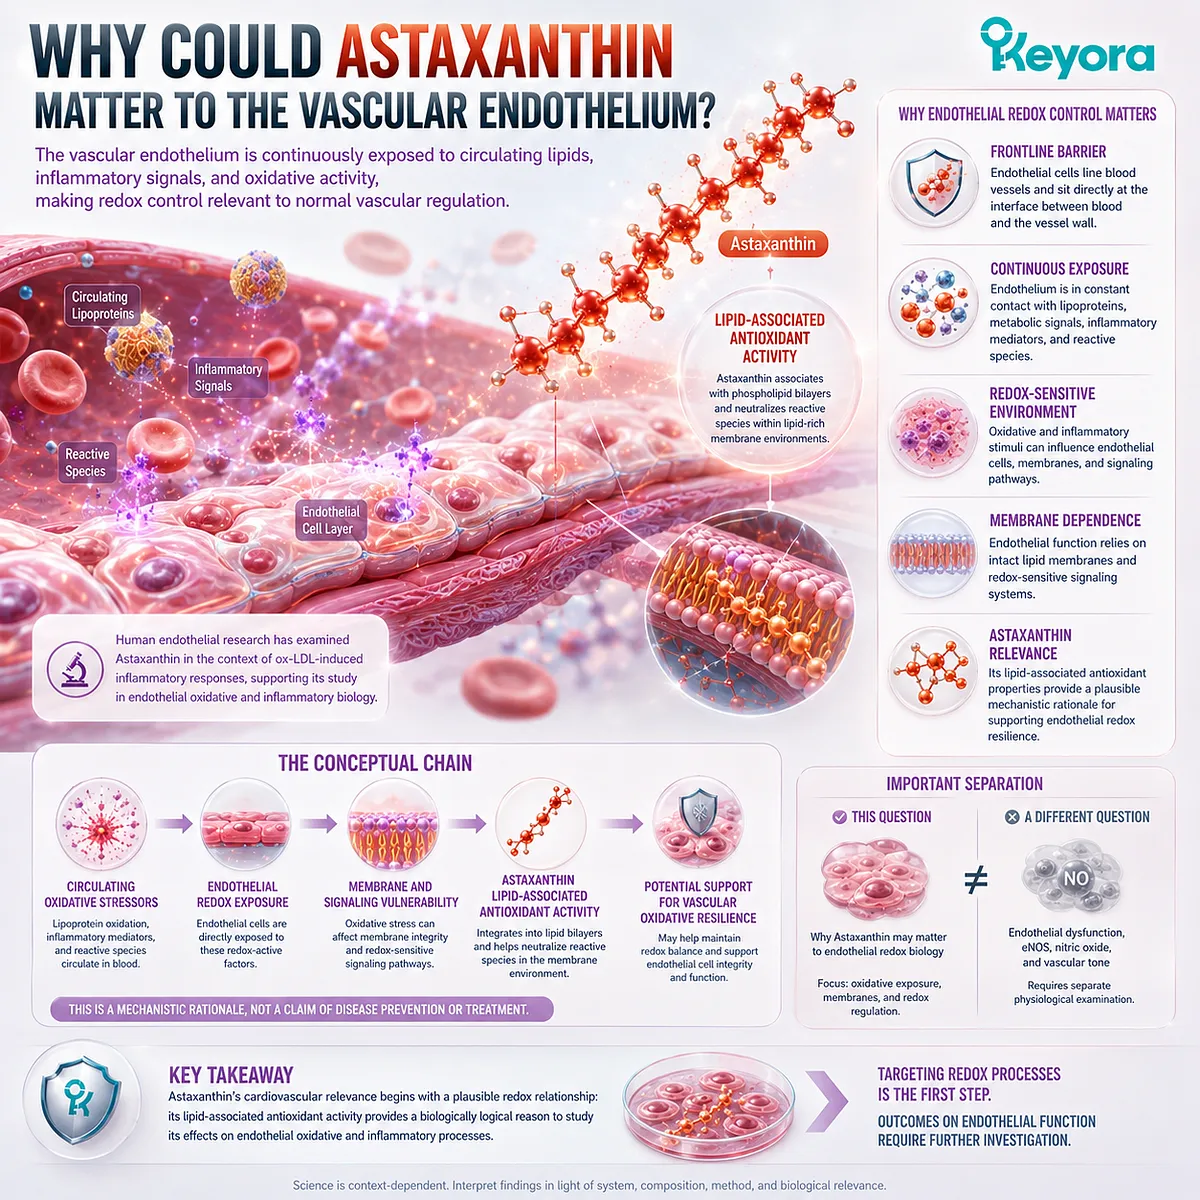
The vascular endothelium is continuously exposed to circulating lipids, inflammatory signals, and oxidative activity, making redox control relevant to normal vascular regulation
The endothelium is the cellular layer lining the inside of blood vessels.
It sits directly at the interface between circulating blood and the vessel wall, placing endothelial cells in continuous contact with lipoproteins, metabolic signals, inflammatory mediators, and reactive species.
This makes vascular redox regulation biologically important.
The previous Q&A established that Astaxanthin can associate with phospholipid bilayers and that its antioxidant chemistry may operate within lipid-rich membrane environments.
In a vascular context, that membrane-associated behavior becomes relevant because endothelial cells rely on intact membranes and redox-sensitive signaling systems for normal function.
The Astaxanthin project source connects the ingredient with endothelial oxidative and inflammatory research and cites work involving ox-LDL-induced inflammatory responses in human endothelial cells.
The appropriate conclusion is not that Astaxanthin automatically “repairs” the endothelium.
Rather, its lipid-associated antioxidant properties provide a mechanistic reason to investigate whether it can influence oxidative processes relevant to endothelial biology.
The conceptual chain is:
Circulating oxidative stressors
↓
Endothelial redox exposure
↓
Membrane and signaling vulnerability
↓
Astaxanthin lipid-associated antioxidant activity
↓
Potential support for vascular oxidative resilience
This section should also be kept distinct from later questions on endothelial dysfunction and nitric oxide.
Astaxanthin’s cardiovascular relevance begins with a plausible redox relationship.
The detailed physiology of endothelial dysfunction, eNOS, nitric oxide, and vascular tone requires separate examination.
How Does Oxidative Stress Connect With Vascular Inflammation?
Oxidative and inflammatory signaling can reinforce one another, which is why inflammatory biomarkers appear in Astaxanthin cardiovascular research
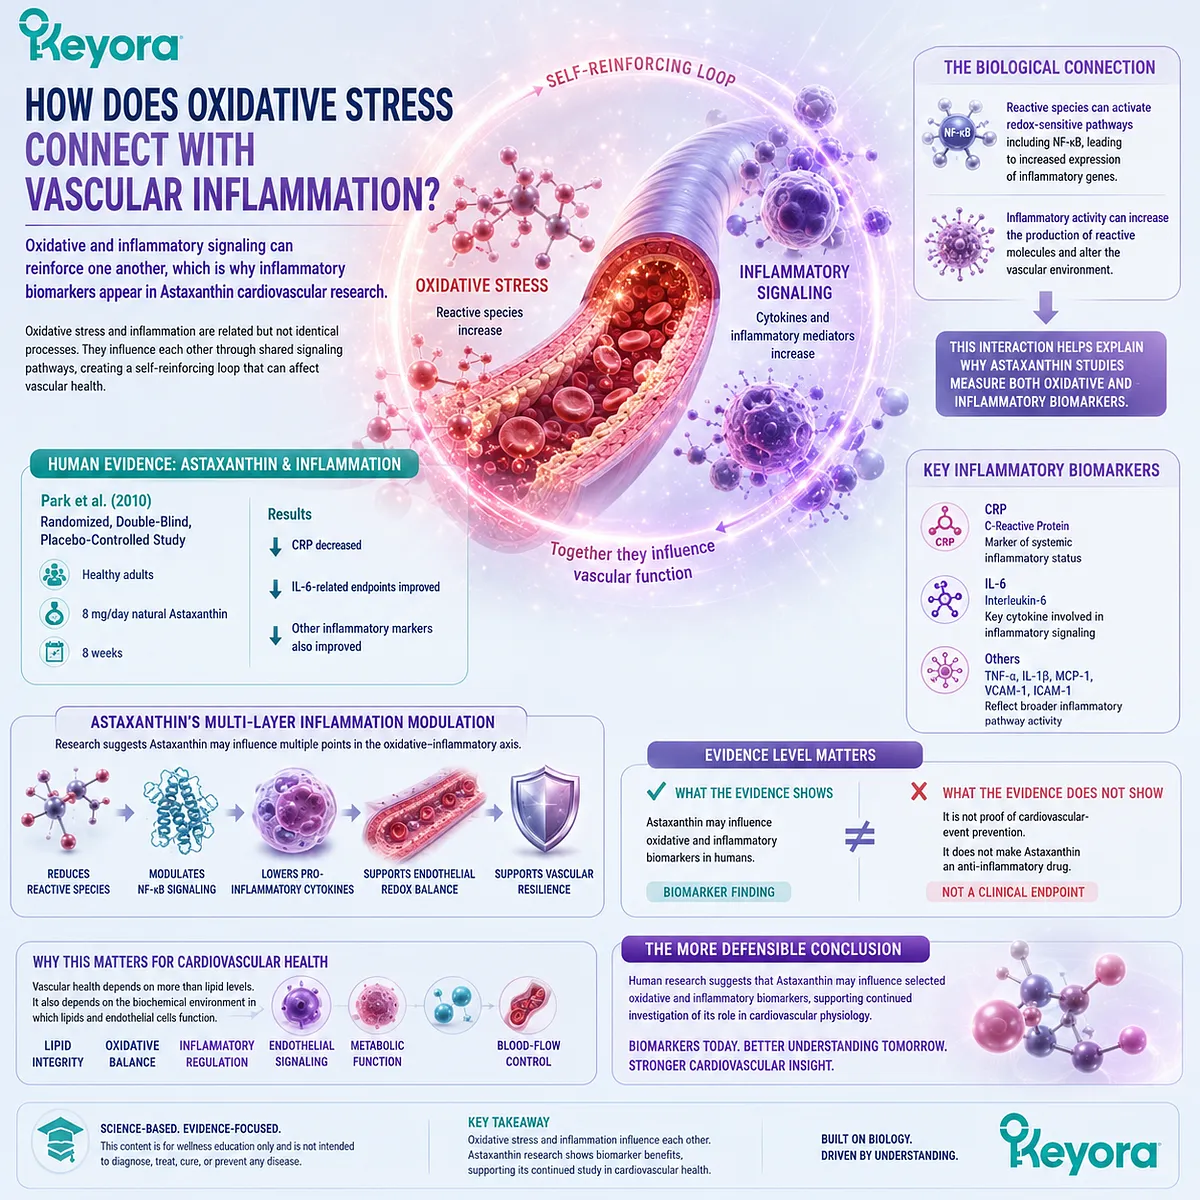
Oxidative stress and inflammation are related but not identical processes.
Reactive species can influence redox-sensitive signaling pathways, while inflammatory activity can alter the production of reactive molecules and the vascular environment.
This interaction is one reason Astaxanthin studies have measured inflammatory biomarkers alongside oxidative-stress endpoints.
The project Astaxanthin source discusses NF-κB-related signaling and cites Park et al. (2010), a randomized, double-blind, placebo-controlled human study. The source describes healthy adults receiving 8 mg/day of natural Astaxanthin for eight weeks and reports reductions in inflammatory measures including CRP, with changes also reported for IL-6-related endpoints.
These findings are relevant because CRP and inflammatory cytokines can provide information about systemic inflammatory status.
But the evidence level must remain clear.
A change in CRP is:
a biomarker finding
not
proof of cardiovascular-event prevention
Likewise, evidence that Astaxanthin influences NF-κB-related biology does not mean it should be described as an anti-inflammatory drug.
The more defensible conclusion is:
Human research suggests that Astaxanthin may influence selected oxidative and inflammatory biomarkers, supporting continued investigation of its role in cardiovascular physiology.
This is an important part of the cardiovascular argument because vascular health is influenced not only by lipid concentrations, but also by the biochemical environment in which lipids and endothelial cells function.
What Do Human Studies Suggest About Lipid Metabolism?
Astaxanthin research extends beyond oxidation into triglycerides, HDL cholesterol, and adiponectin-related metabolic regulation
Astaxanthin cardiovascular research also includes metabolic endpoints.
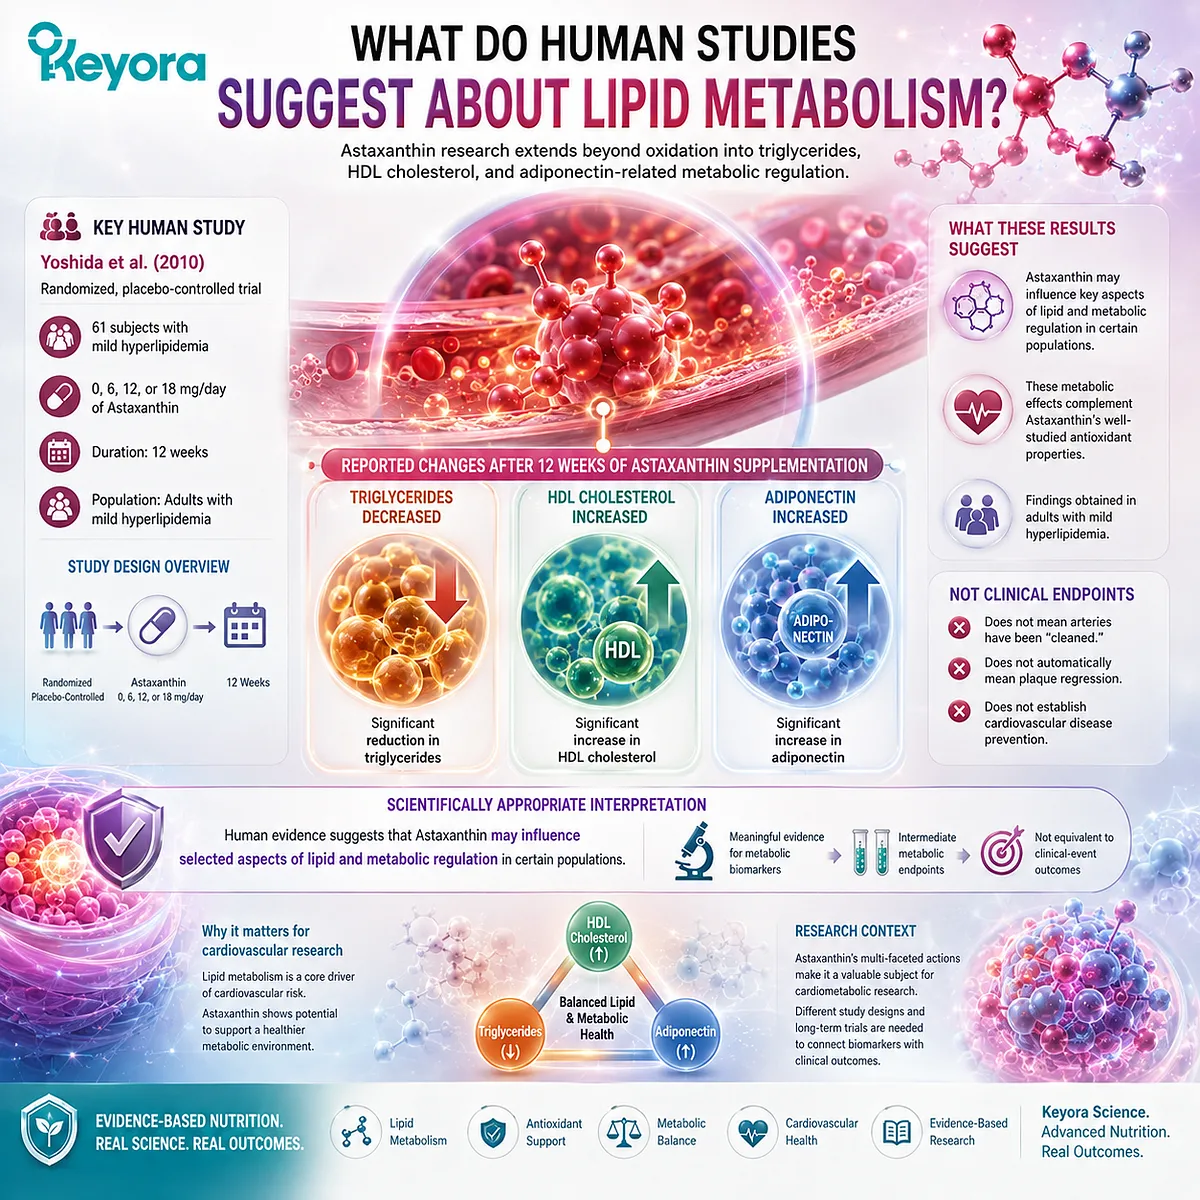
One of the clearest human studies cited in the project source is Yoshida et al. (2010).
According to the source, 61 subjects with mild hyperlipidemia participated in a randomized, placebo-controlled trial and received 0, 6, 12, or 18 mg/day of Astaxanthin for 12 weeks.
The source reports changes in three notable endpoints:
Triglycerides
↓
HDL cholesterol
↑
Adiponectin
↑
The Keyora summary likewise identifies reductions in triglycerides and increases in HDL cholesterol and adiponectin among the reported findings.
These results broaden the Astaxanthin cardiovascular story.
The ingredient is not only being studied as a molecule that interacts with oxidative chemistry. It has also been investigated for possible effects on the metabolic lipid environment.
However, these findings require careful interpretation.
An increase in HDL cholesterol does not mean that arteries have been “cleaned.”
A reduction in triglycerides does not automatically mean plaque regression.
And an increase in adiponectin does not establish cardiovascular disease prevention.
These are intermediate metabolic endpoints.
The appropriate conclusion is:
Human evidence suggests that Astaxanthin may influence selected aspects of lipid and metabolic regulation in certain populations.
That makes the ingredient relevant to cardiovascular research, but it does not turn metabolic biomarkers into clinical-event outcomes.
What Does the Research Suggest About Blood Pressure, Blood Flow, and Vascular Function?
Human studies have explored hemodynamic outcomes, but observed vascular changes must be separated from proposed antioxidant mechanisms
A further layer of Astaxanthin cardiovascular research concerns vascular function rather than lipid chemistry alone.
The Keyora source describes Iwabayashi et al. (2009), an eight-week human study using 12 mg/day of Astaxanthin in participants screened for elevated oxidative-stress burden.
The source reports an approximate 7 mmHg reduction in systolic blood pressure and an approximate 4 mmHg reduction in diastolic blood pressure, alongside changes in oxidative-stress markers.
Another cited study, Miyawaki et al. (2008), examined 6 mg/day of Astaxanthin over 10 days and evaluated blood-rheology-related measures. The Keyora summary reports improvement in transit-time-related measurements.
These findings are interesting because they move beyond molecular oxidation into physiological measurements.
But they also demonstrate why evidence interpretation matters.
The observed findings were blood-pressure and rheology-related endpoints.
The proposed mechanisms include:
-
oxidative-stress modulation;
-
endothelial redox effects;
-
nitric-oxide-related signaling;
-
membrane-associated antioxidant activity.
Those mechanisms are biologically plausible, but they should not automatically be treated as directly proven causes of the observed changes.
For example, the EP-3 source presents a detailed model involving BH4 oxidation, eNOS uncoupling, superoxide production, and nitric oxide preservation.
That model can help explain why Astaxanthin is investigated in vascular research.
It does not mean the blood-pressure study directly demonstrated every step of that pathway.

How Strong Is the Human Cardiovascular Evidence for Astaxanthin?
Human evidence is promising at the biomarker and physiological level, but it is not equivalent to evidence from cardiovascular outcome trials
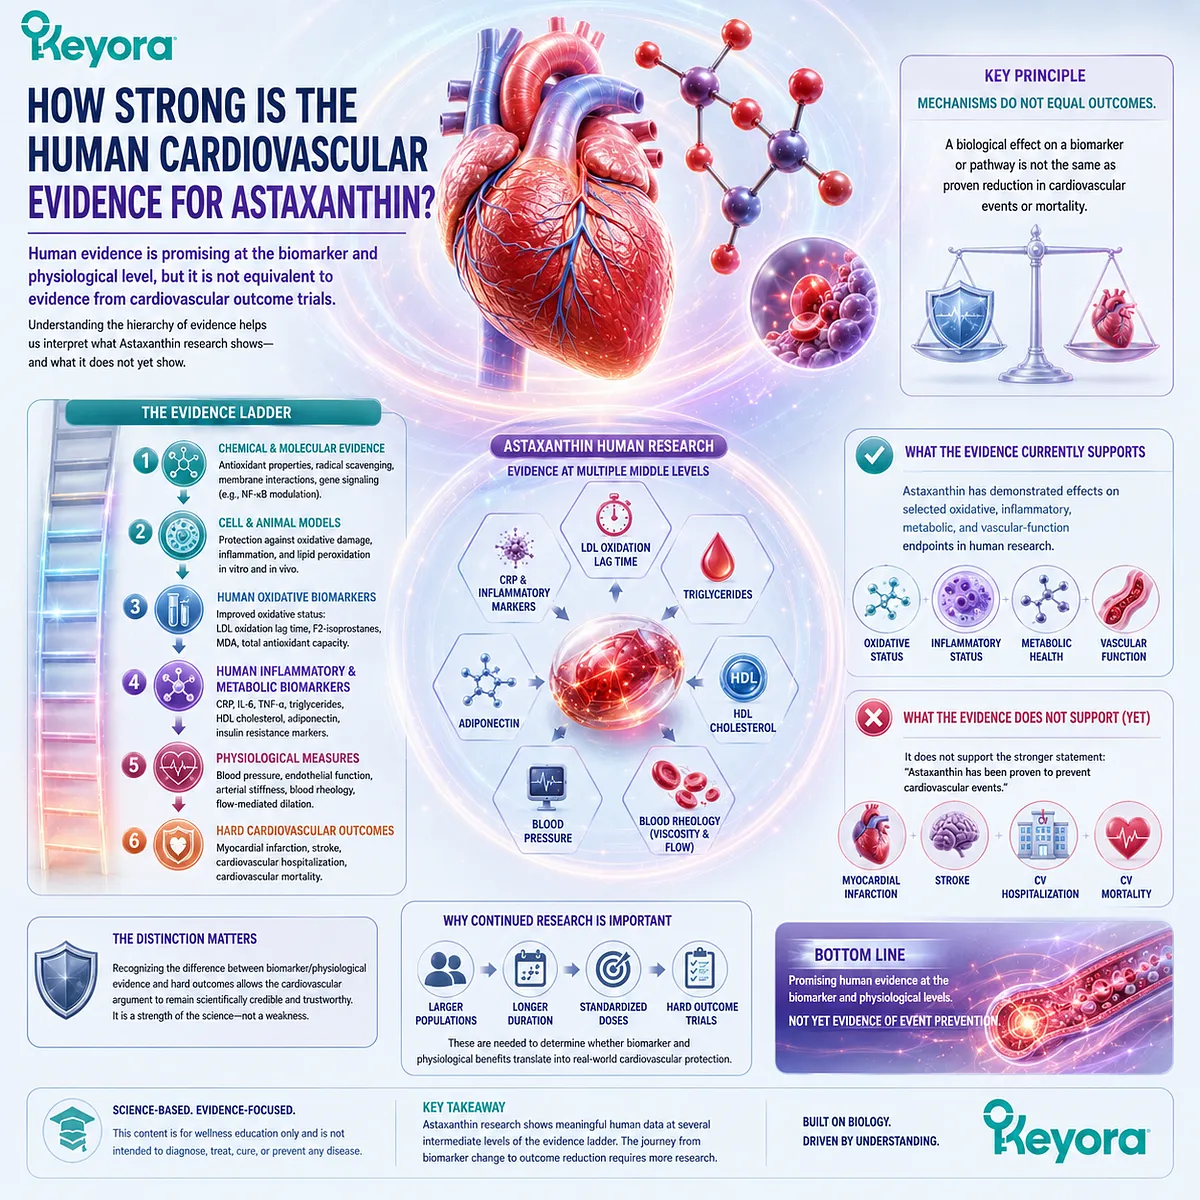
The strength of the Astaxanthin cardiovascular case depends on understanding the hierarchy of evidence.
The Keyora EP-3 source itself states an important principle:
Mechanisms do not equal outcomes.
A useful evidence ladder is:
Chemical and molecular evidence
↓
Cell and animal models
↓
Human oxidative biomarkers
↓
Human inflammatory and metabolic biomarkers
↓
Physiological measures such as blood pressure or blood rheology
↓
Hard cardiovascular outcomes
The available project sources contain evidence at several of the middle levels.
They include human data relating to:
-
LDL oxidation lag time;
-
CRP and other inflammatory measures;
-
triglycerides;
-
HDL cholesterol;
-
adiponectin;
-
blood pressure;
-
blood-rheology-related measures.
That is a meaningful research base.
But it is not the same as large, long-duration randomized trials showing reduced:
-
myocardial infarction;
-
stroke;
-
cardiovascular hospitalization;
-
cardiovascular mortality.
This distinction should not be treated as a weakness to hide.
It is what allows the cardiovascular argument to remain scientifically credible.
The evidence currently supports the statement:
Astaxanthin has demonstrated effects on selected oxidative, inflammatory, metabolic, and vascular-function endpoints in human research.
It does not support the stronger statement:
Astaxanthin has been proven to prevent cardiovascular events.
Those two claims belong to different evidence levels.
Recognizing the difference is essential for responsible nutritional interpretation.
Does Astaxanthin Prevent Heart Disease—or What Can We Actually Conclude?
Astaxanthin has a credible cardiovascular research rationale, but current evidence supports physiological relevance rather than proven heart-disease prevention
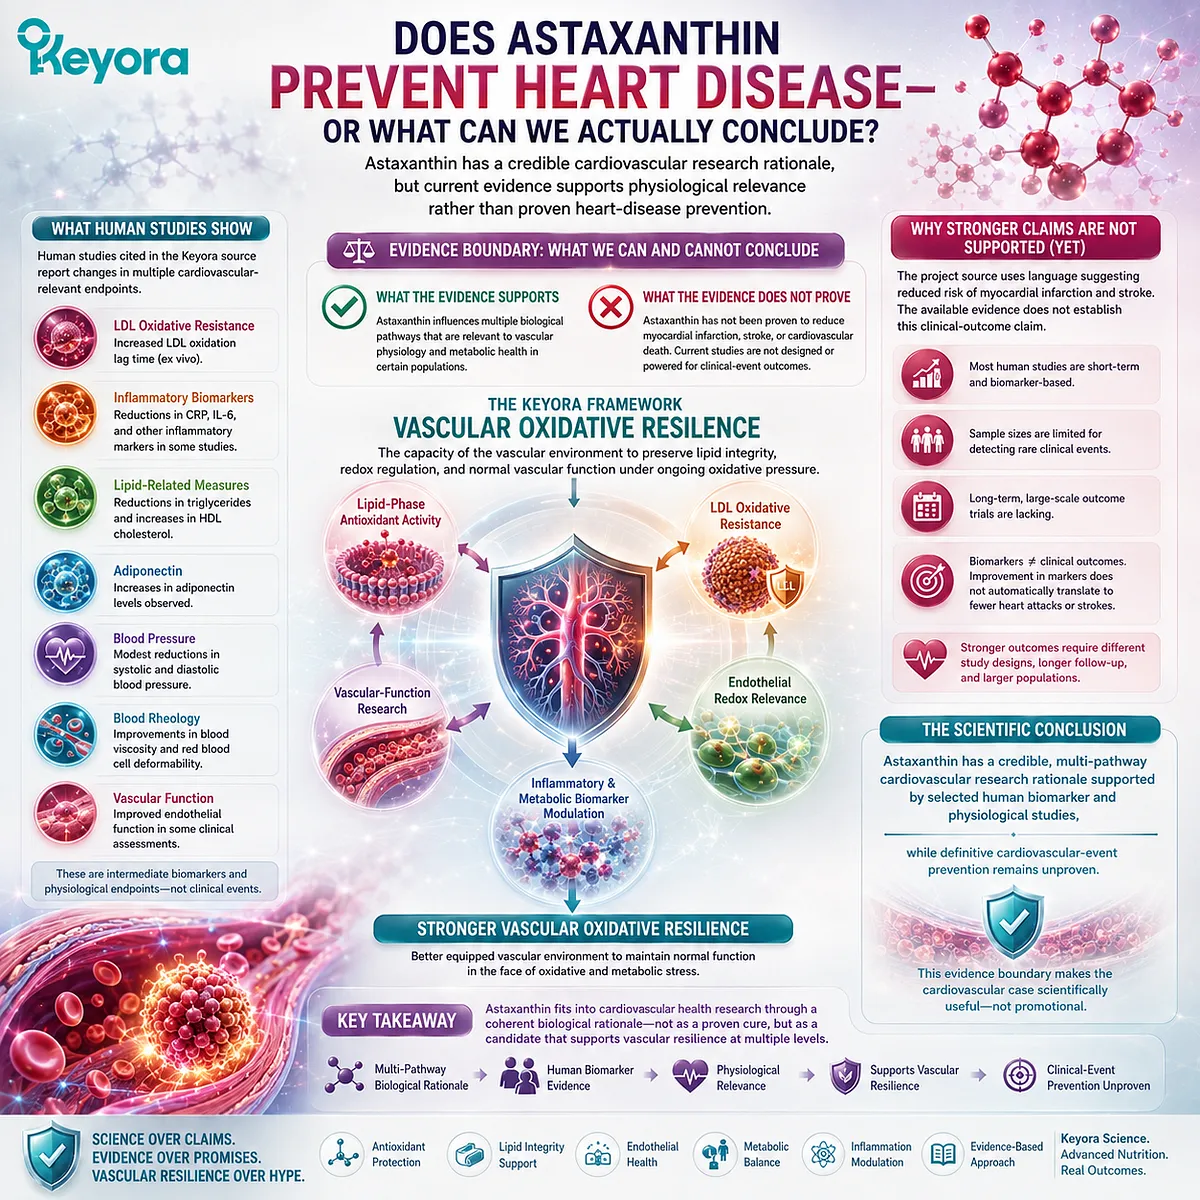
The available evidence supports a clear but bounded conclusion.
Astaxanthin is scientifically relevant to cardiovascular research because several of its biological properties intersect with processes that matter in vascular physiology.
Human studies cited in the Keyora source report changes in LDL oxidative resistance, inflammatory biomarkers, lipid-related measures, adiponectin, blood pressure, and blood-rheology-related endpoints.
However, the project Astaxanthin source also uses stronger language suggesting reduced risk of myocardial infarction and stroke.
The nearby evidence presented in these source materials does not establish that clinical-outcome claim.
The more defensible Keyora framework is Vascular Oxidative Resilience:
the capacity of the vascular environment to preserve lipid integrity, redox regulation, and normal vascular function under ongoing oxidative pressure
Astaxanthin fits this framework through:
Lipid-phase antioxidant activity
↓
LDL oxidative resistance
Endothelial redox relevance
Inflammatory and metabolic biomarker modulation
Vascular-function research
↓
Vascular Oxidative Resilience
The conclusion is therefore not:
Astaxanthin prevents cardiovascular disease.
It is:
Astaxanthin has a credible, multi-pathway cardiovascular research rationale supported by selected human biomarker and physiological studies, while definitive cardiovascular-event prevention remains unproven.
That evidence boundary is precisely what makes the cardiovascular case scientifically useful rather than promotional.
This article is for educational and informational purposes only. It does not provide medical advice, diagnosis, treatment, cure, prevention, disease outcome claims, hormone restoration claims, fertility outcome claims, or formula-specific clinical efficacy claims.