
What Do CK, LDH, and MDA Tell Us About Exercise Recovery?
Keyora Research Q&A Library
This is part of the Keyora Research Q&A Series, derived from Keyora Astaxanthin Research Journal Series.
Within the Keyora Astaxanthin Researcn framework, this Q&A translates complex astaxanthin biology into reader-friendly, evidence-bound answers, focusing on natural astaxanthin identity, molecular structure, antioxidant and redox mechanisms, membrane lipid interaction, mitochondrial resilience, inflammatory signaling pathways, human evidence interpretation, and the scientific principles behind responsible supplementation.
First published by Keyora Research Journal: www.keyorahealth.com

Direct Answer
CK, LDH, and MDA provide different biochemical clues about how the body responds to exercise stress. They should not be treated as interchangeable markers, and none of them measures the entire recovery process.
Within Keyora Astaxanthin EP-4: The Cardiac Architecture: Bio-Energetic Sovereignty, CK and LDH are used primarily as indicators related to exercise-associated tissue and muscle stress, while MDA is used as a marker of lipid peroxidation.
In the human study by Baralic et al. (2015) summarized in EP-4, 40 young elite soccer players received 4 mg of natural Astaxanthin daily for 90 days.
The Astaxanthin group showed lower CK, lower LDH, lower MDA, and a smaller rise in CRP.
These findings support the interpretation that the supplemented athletes showed a different and potentially more favorable biochemical response to repeated exercise stress.
But the biomarkers must remain attached to what they can actually tell us.
-
Lower CK does not automatically prove faster muscle repair.
-
Lower LDH does not establish complete tissue protection.
-
Lower MDA does not mean oxidative stress or lipid peroxidation disappeared.
And none of these markers, by itself, proves that an athlete felt less sore, experienced less fatigue, or returned to full performance sooner.
The central rule is simple:
A biomarker tells us about the biological signal it measures, not the entire recovery experience.

What Does CK Tell Us After Exercise?
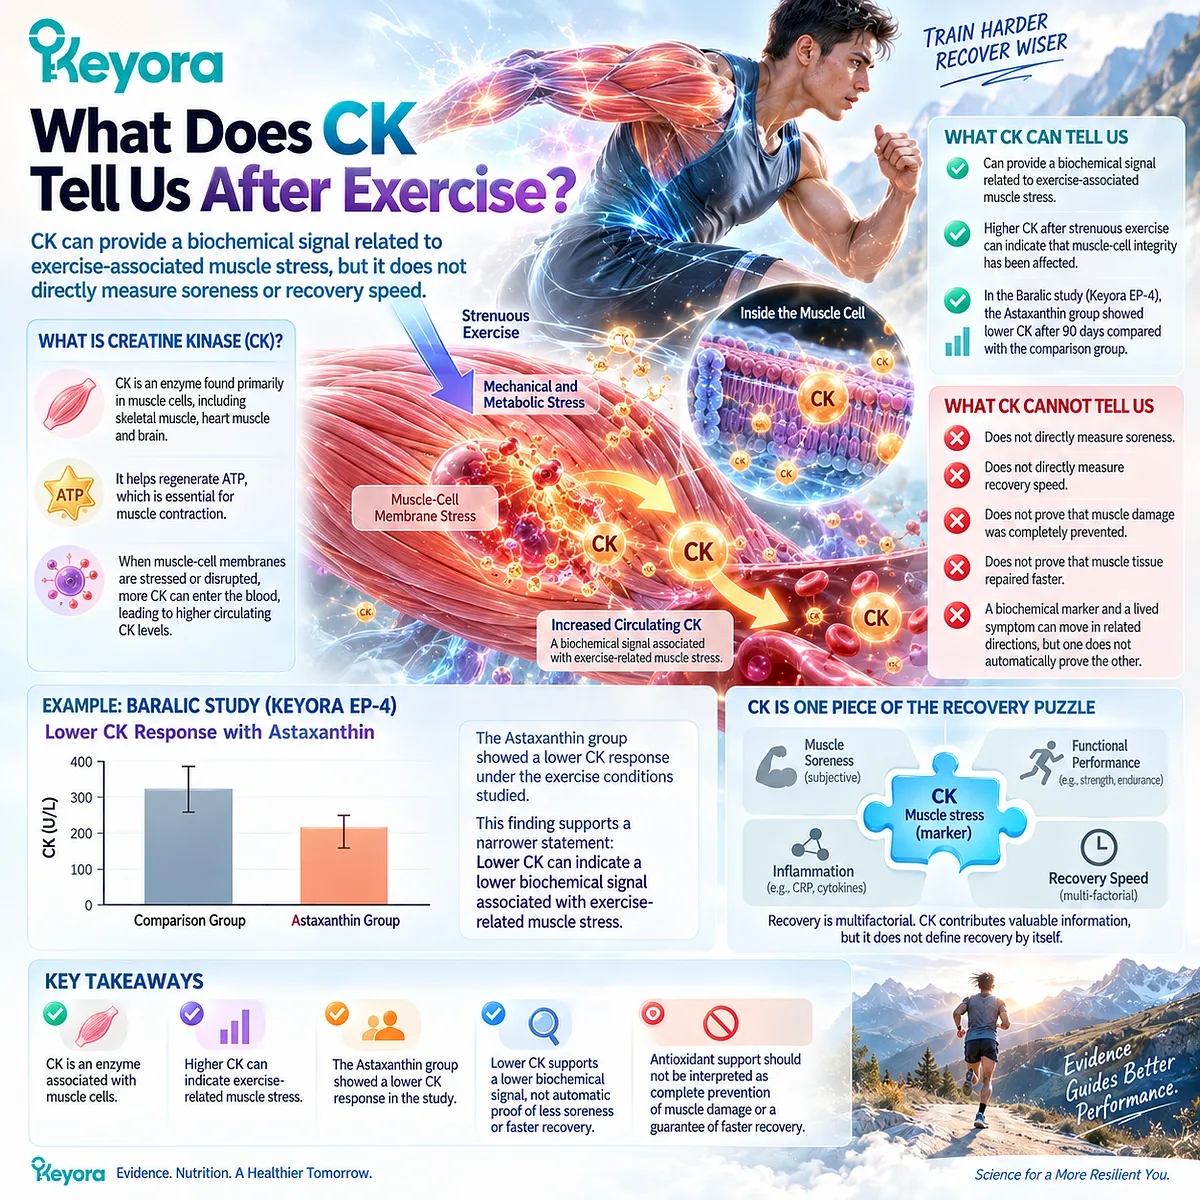
CK can provide a biochemical signal related to exercise-associated muscle stress, but it does not directly measure soreness or recovery speed
In the EP-4 recovery framework, creatine kinase, or CK, is presented as an enzyme associated with muscle cells and is used as one marker of exercise-related muscle stress.
The source describes higher circulating CK as evidence that strenuous exercise has affected muscle-cell integrity.
The Baralic study becomes relevant because the Astaxanthin group showed lower CK after the 90-day intervention than the comparison group in the EP-4 summary.
That finding can reasonably support a narrower statement:
The Astaxanthin group showed a lower CK response under the exercise conditions studied.
The next step is where interpretation becomes important.
EP-4 translates lower CK into stronger claims about fewer cells rupturing and greater structural preservation.
For public evidence communication, that interpretation should remain more cautious.
Lower CK can support a lower biochemical signal associated with exercise-related muscle stress.
It should not automatically become:
muscle damage was completely prevented
or:
muscle tissue repaired faster
or:
the athlete experienced less soreness
Those are different questions.
A biochemical marker and a lived symptom can move in related directions, but one does not automatically prove the other.
This is especially important in exercise recovery because consumers often interpret a lower “damage marker” as meaning that the body has already recovered.
That conclusion is too broad.
CK contributes one piece of evidence.
It does not define recovery by itself.
What Does LDH Tell Us After Exercise?
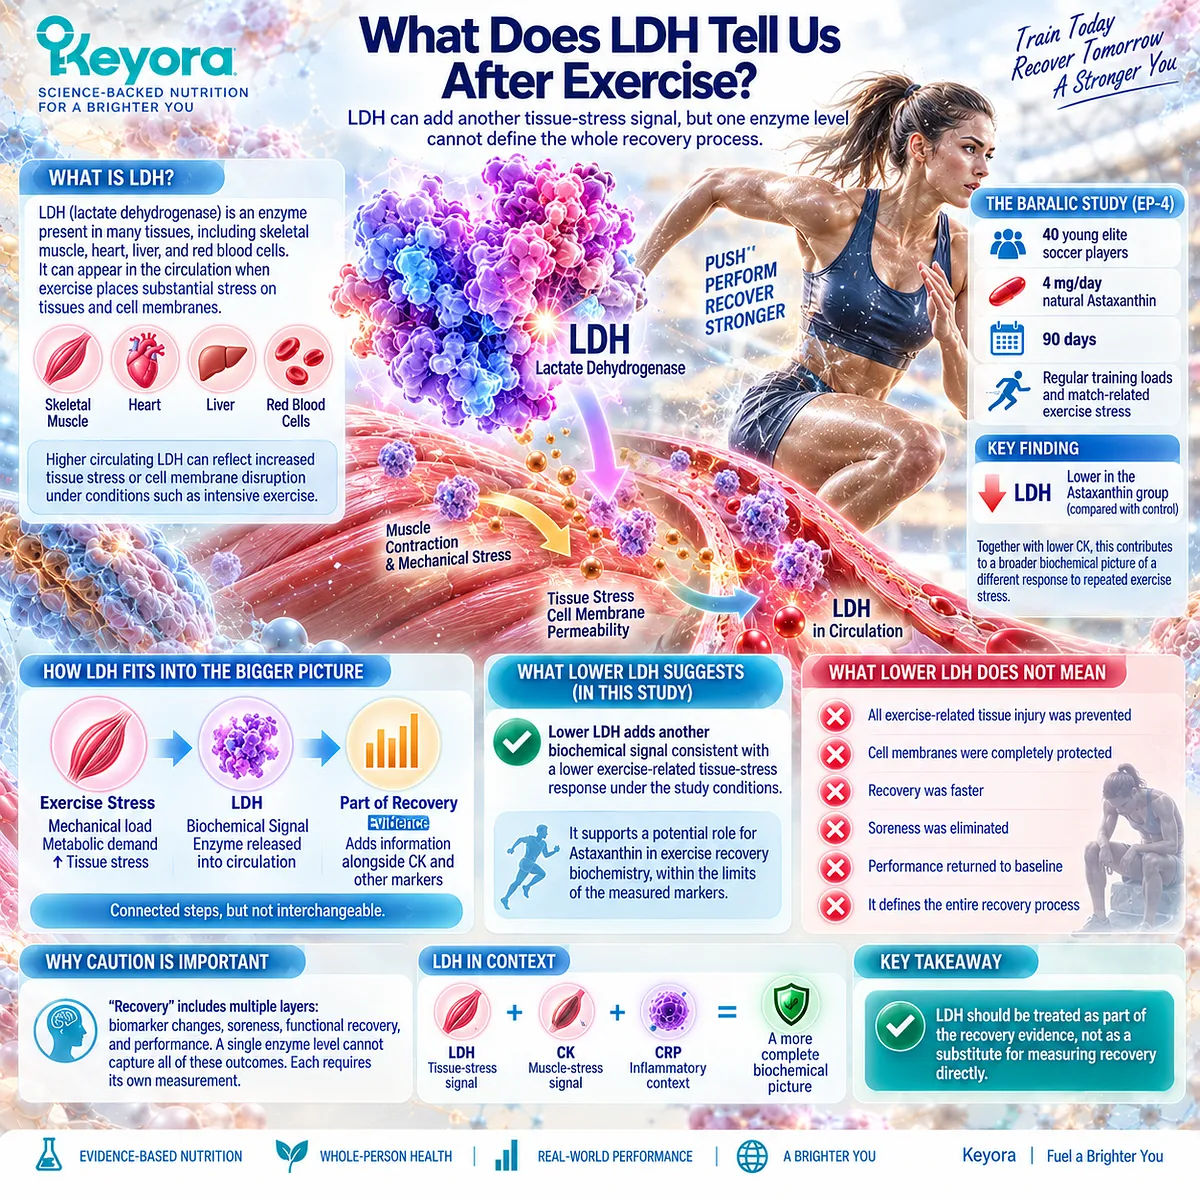
LDH can add another tissue-stress signal, but one enzyme level cannot define the whole recovery process
LDH, or lactate dehydrogenase, appears alongside CK in the EP-4 exercise-recovery discussion.
The source describes LDH as another enzyme that can appear in the circulation when exercise places substantial stress on tissues and cell membranes.
In the Baralic study summary, LDH was also lower in the Astaxanthin group.
When CK and LDH both move in a favorable direction, they can contribute to a broader biochemical picture suggesting a different response to repeated exercise stress.
But LDH should not be treated as a complete diagnosis of what happened to the athlete.
The scientifically safer interpretation is:
Lower LDH adds another biochemical signal consistent with a lower exercise-related tissue-stress response under the study conditions.
It should not automatically be translated into:
all exercise-related tissue injury was prevented
cell membranes were completely protected
or:
recovery was faster
The distinction matters because the word “recovery” contains several layers.
A blood marker may change.
A person may still experience soreness.
Performance may or may not have returned to baseline.
Those outcomes require their own measurements.
EP-4 combines lower CK and LDH with the broader concept of structural resilience. That is a useful framework for understanding why the findings might matter, but the measured evidence itself remains biochemical.
Therefore, LDH should be treated as part of the recovery evidence, not as a substitute for measuring recovery directly.
What Does MDA Tell Us About Oxidative Stress?
MDA reflects a lipid-peroxidation signal, not the total amount of exercise stress or all ROS activity
MDA, or malondialdehyde, plays a different role from CK and LDH in the EP-4 framework.
The source uses MDA as a marker associated with lipid peroxidation rather than primarily as a muscle-stress enzyme.
In the Baralic study summary, MDA was lower in the Astaxanthin group after the intervention.
That supports an evidence-matched interpretation:
The Astaxanthin group showed a lower measured lipid-peroxidation signal under repeated athletic stress.
This is not the same as saying that oxidative stress disappeared.
EP-4 uses stronger language, interpreting lower MDA as evidence that cell membranes did not oxidize and placing the result within its Oxidative Buffer concept.
For biomarker interpretation, the more precise conclusion is narrower.
Lower MDA ≠ zero lipid peroxidation
and:
Lower MDA ≠ elimination of all exercise-generated ROS
MDA provides information about one oxidative-stress-related pathway within the conditions studied.
It does not measure every reactive species, every tissue, or every aspect of exercise recovery.
The same boundary applies to symptoms.
A lower MDA level does not automatically establish:
-
less muscle soreness
-
less fatigue
or:
-
faster restoration of athletic performance
Those outcomes belong to different evidence domains.
This is why CK, LDH, and MDA should not be grouped together simply as “damage markers.”
They answer different biochemical questions.

Why Better Biomarkers Do Not Automatically Mean Faster Recovery
Biochemical improvement and lived recovery are related questions, not identical endpoints
The Baralic findings create a compelling pattern:
-
CK lower
-
LDH lower
-
MDA lower
with a smaller rise in CRP also reported in the EP-4 summary.
It is reasonable to describe this as a more favorable exercise-stress biomarker profile.
The mistake occurs when the interpretation immediately jumps from:
better biomarkers
to:
faster recovery
EP-4 makes that jump explicitly through the sequence:
less damage → faster recovery → higher frequency of performance.
That sequence is biologically understandable as a hypothesis.
It should not be presented as if every step was directly measured by the biomarkers.
To establish less soreness, soreness needs to be assessed.
To establish less fatigue, fatigue needs to be measured.
To establish faster return to performance, exercise performance needs to be reassessed during the recovery period.
To establish clinical tissue repair, direct evidence of that clinical outcome would be required.
Therefore:
biomarker improvement can strengthen a recovery hypothesis without completing the recovery claim
This distinction helps prevent both underinterpretation and overinterpretation.
The biomarkers are not meaningless.
They provide useful evidence about biological response.
But they should not be asked to answer questions they were not designed to answer.
A lower CK, LDH, or MDA result can therefore be scientifically meaningful while remaining only one layer of the recovery story.

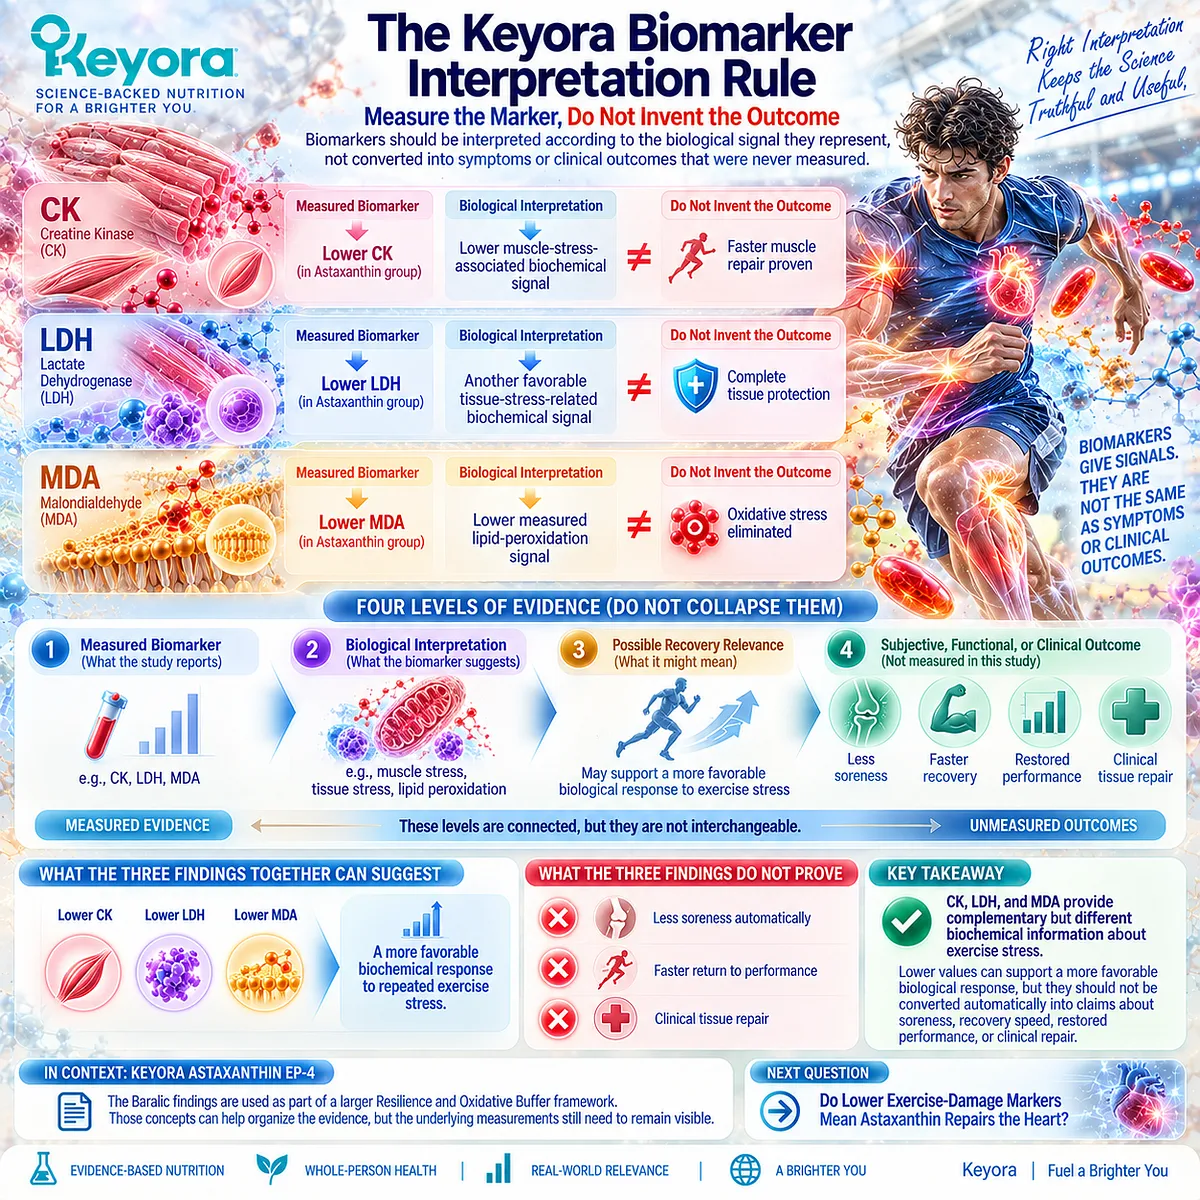
The Keyora Biomarker Interpretation Rule: Measure the Marker, Do Not Invent the Outcome
Biomarkers should be interpreted according to the biological signal they represent, not converted into symptoms or clinical outcomes that were never measured
The Keyora Biomarker Interpretation Rule separates four levels of evidence:
measured biomarker
↓
biological interpretation
↓
possible recovery relevance
↓
subjective, functional, or clinical outcome
The critical rule is that these levels should not be collapsed into one another.
For CK:
Lower CK
→ lower muscle-stress-associated biochemical signal
≠ faster muscle repair proven
For LDH:
Lower LDH
→ another favorable tissue-stress-related biochemical signal
≠ complete tissue protection
For MDA:
Lower MDA
→ lower measured lipid-peroxidation signal
≠ oxidative stress eliminated
And when the three findings are considered together:
better biomarkers
≠ less soreness automatically
better biomarkers
≠ faster return to performance
better biomarkers
≠ clinical tissue repair
This is particularly important because Keyora Astaxanthin EP-4 uses the Baralic findings as part of a larger Resilience and Oxidative Buffer framework.
Those concepts can help organize the evidence.
But the underlying measurements still need to remain visible.
The strongest conclusion is therefore:
CK, LDH, and MDA provide complementary but different biochemical information about exercise stress.
Lower values can support a more favorable biological response, but they should not be converted automatically into claims about soreness, recovery speed, restored performance, or clinical repair.
That evidence boundary leads directly to the next question:
Do Lower Exercise-Damage Markers Mean Astaxanthin Repairs the Heart?
This article is for educational and informational purposes only. It does not provide medical advice, diagnosis, treatment, cure, prevention, disease outcome claims, hormone restoration claims, fertility outcome claims, or formula-specific clinical efficacy claims.